
Blocked Tear Duct Surgery

Author: Doç. Dr. Elif Ceren Yeşilkaya, Ophthalmologist, Cornea and Refractive Surgery
Published: · Last updated:
A blocked tear duct causes watering and discharge. Babies are treated with massage and probing; adults may need DCR surgery to create a new drainage route.
Quick Answer
A blocked tear duct means the channel that drains tears from the eye into the nose has closed, causing constant watering, discharge and repeated infections. In babies it usually opens by itself; in adults a lasting blockage is treated with dacryocystorhinostomy (DCR).
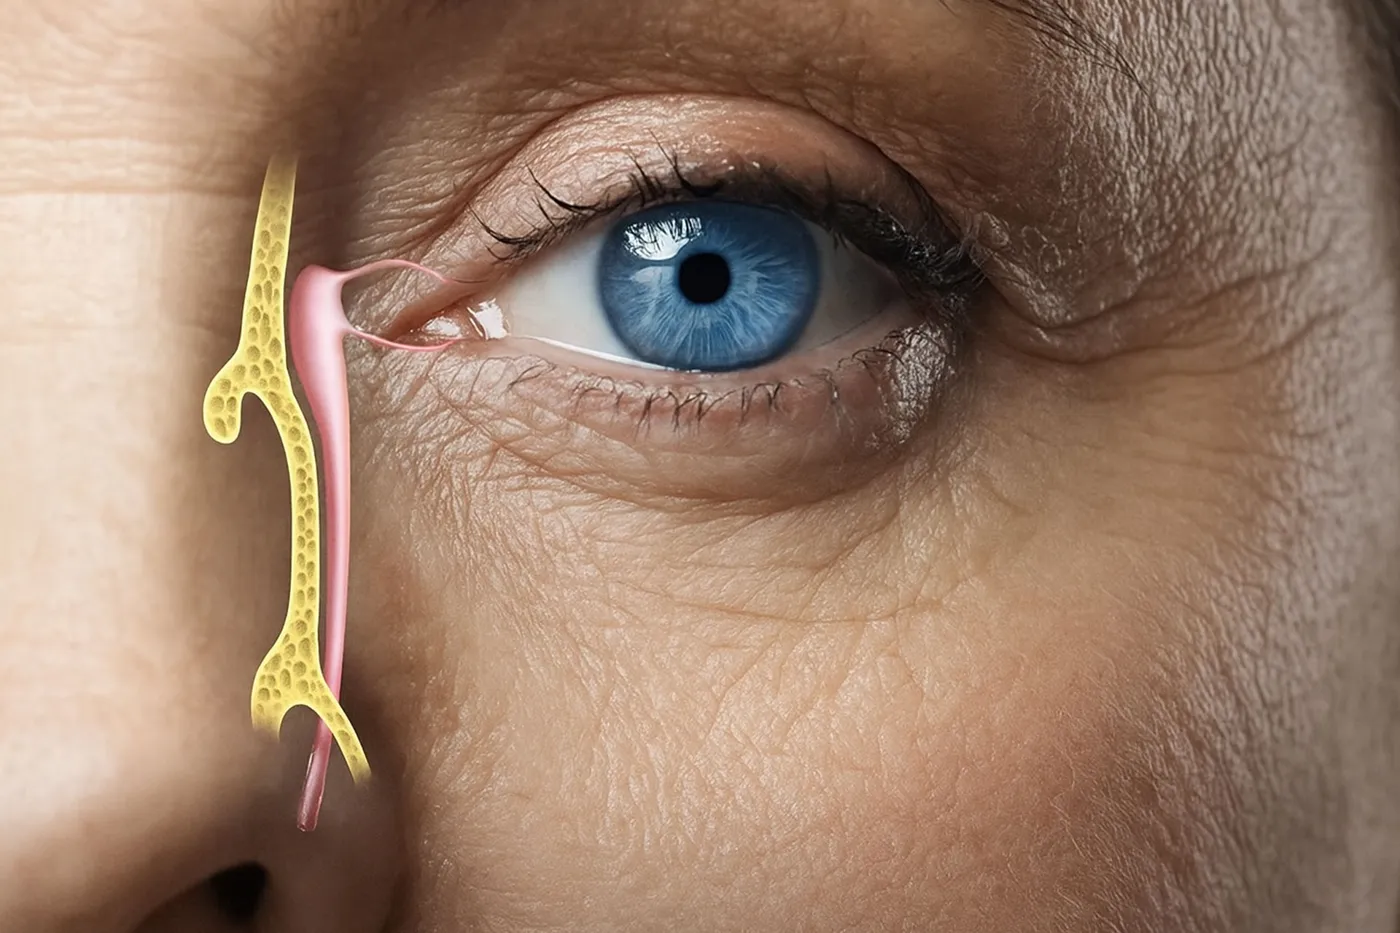
How do tears drain from the eye?
Tears leave the eye through two tiny openings (puncta) at the inner corners of the upper and lower lids. They pass along narrow channels into the tear sac, which sits beside the nose, and from there the nasolacrimal duct carries them down into the nasal cavity. That is why your nose runs when you cry. If the route narrows or closes at any point, tears have nowhere to go and spill over onto the cheek.
Why does a blocked duct cause watering and discharge?
The classic sign is a watering eye when you are not crying, known as epiphora. Tears that sit in the sac are a good breeding ground for bacteria, so the watering often comes with crusting and sticky discharge. Other symptoms include:
- redness and irritation along the lid margin and lash line
- swelling around the eye, especially at the inner corner
- burning or stinging
- symptoms that worsen in cold or windy weather
- occasionally, a painful red swelling at the inner corner (dacryocystitis, an infection of the tear sac)
A blockage can be present from birth or develop later. Acquired blockages are linked to age-related tissue changes, past infection or inflammation, injuries to the face and nose and, rarely, tumours.
A watering eye is not always blocked. Dry eye irritates the surface and triggers reflex tearing. A lower lid that turns outwards or a narrowed punctum can also stop tears from entering the drainage system. Treatment is chosen once the source of the watering has been found.
Blocked tear ducts in babies
In some babies, a thin membrane at the lower end of the duct, where it opens into the nose, has not opened by birth. Watering and stickiness usually start in the first few weeks. Most of these blockages open by themselves within the first year.
Massage and cleaning
Massaging the tear sac is recommended during this time. Place your index finger between the inner corner of the eye and the bridge of the nose and slide it downwards with gentle pressure. The aim is to build pressure in the sac and push the membrane open. Clean away crusts with a clean cotton pad moistened with boiled and cooled water, wiping from the inner corner outwards. Antibiotic drops may be prescribed if the discharge becomes heavy.
Probing
If the duct is still blocked around the first birthday despite massage, probing is carried out. A fine probe is passed down the duct to open the membrane. If the blockage comes back, probing can be repeated with a silicone tube placed in the duct or with balloon dilation.
If watering comes with sensitivity to light, or you notice that the eye looks enlarged or the cornea looks cloudy, do not wait, as these are signs seen in congenital glaucoma. A red swelling at the inner corner or a fever also needs to be seen the same day.
How is the blockage located in adults?
The examination starts with the position of the lids, the puncta and the surface of the eye. During lacrimal irrigation, saline is gently flushed into a punctum through a fine tip. If you taste it in your throat, the route is open. If it flows back, the route is blocked, and where it comes back from shows the level of the blockage. A fluorescein dye test, which tracks how quickly tears clear from the eye, may also be used. If endoscopic surgery is being considered, the inside of the nose is examined, and imaging is requested if an injury or growth is suspected.
Assoc. Prof. Dr. Elif Ceren Yeşilkaya plans treatment based on these findings. For a mild, recent blockage, warm compresses, sac massage and antibiotics for any infection come first. A partial narrowing may respond to probing or balloon dilation. A complete, lasting blockage, or one that keeps causing infections, needs surgery. Surgery is not done while the sac is infected; the infection is cleared with antibiotics first.
How is dacryocystorhinostomy (DCR) done?
DCR bypasses the blocked duct. A new opening is made through the thin bone between the tear sac and the nasal cavity, so tears drain straight into the nose. There are two approaches.
External DCR
A small incision is made on the side of the nose, close to the inner corner of the eye. The surgeon opens the passage with the sac and bone in direct view and stitches the wall of the sac to the lining of the nose. The skin stitches are removed at a follow-up visit.
Endoscopic DCR
A thin camera (endoscope) is passed through the nostril and the new opening is made from inside the nose. There is no cut on the skin. The anatomy inside the nose, such as a markedly deviated septum, affects whether this route is suitable.
Silicone tube
In most operations a fine silicone tube is placed to stop the new channel from closing while it heals. It runs from the upper and lower puncta down into the nose and may be visible as a thin loop at the inner corner of the eye. It is removed in clinic once the channel has healed, and your doctor decides when. Do not pull on it, and let the clinic know if it seems to have slipped.
If the small channels from the puncta are also blocked, a standard DCR may not be enough and a different surgical plan is needed.
After DCR
In the early days, expect mild swelling, bruising and discomfort at the inner corner and side of the nose, and possibly some blood-stained discharge from the nose. Avoid blowing your nose hard and skip strenuous exercise until your doctor tells you otherwise. Use your eye drops, nasal spray or nasal rinse regularly, and keep the area around the eye and inside the nose clean. At follow-up visits, irrigation is used to check that the new channel is open.
Possible risks include nosebleeds, infection, a skin scar after the external approach, the tube slipping out of place and the new channel gradually narrowing and closing. If it closes, further surgery may be needed.
Seek help promptly if you have:
- a nosebleed that will not stop or is getting heavier
- a painful, red swelling at the inner corner that is growing quickly, or a fever
- redness and swelling spreading to the eyelid and cheek
- reduced vision or pain when moving the eye
Your first appointment takes place at Medicana Zincirlikuyu (Şişli, Istanbul). At that visit, lacrimal irrigation shows whether the tear duct is blocked and at what level.
{ AI · preliminary guidance }
onlineLet's talk about your eyelids
AI responses do not replace a medical diagnosis.
Frequently Asked Questions
-
My baby's eye is always watery and sticky. Is it a blocked tear duct?
That is the most common sign of a congenital blocked tear duct, and most clear up on their own within the first year. Your baby should still be examined. Sensitivity to light, an eye that looks enlarged or a cloudy cornea can be signs of congenital glaucoma and need to be checked without delay.
-
How do I massage my baby's tear sac?
Place your index finger between the inner corner of the eye and the bridge of the nose, press gently and slide it downwards towards the nose. Do this a few times a day, with several strokes each time. The right spot and pressure are shown to you at the examination.
-
At what age is probing done?
If the duct is still blocked despite massage, probing is usually planned around the first birthday. It may be considered earlier in babies who keep getting infections. How the procedure is carried out is explained in detail at the examination.
-
What is the difference between external and endoscopic DCR?
Both create a new opening between the tear sac and the inside of the nose. External DCR uses a small skin incision at the side of the nose. Endoscopic DCR is done through the nostril with a camera and leaves no cut on the skin. The choice depends on where the blockage is, the anatomy inside your nose and any previous surgery.
-
How is the silicone tube removed?
It is taken out in clinic, and most people feel only a slight tugging sensation. When it comes out depends on how the new channel is healing, and your doctor decides the timing at your check-ups.
-
Can I blow my nose after DCR?
Avoid blowing your nose hard after surgery, as it can set off bleeding. Use the nasal spray or rinse you are given exactly as instructed. You will be told at your check-up when normal nose-blowing is fine.
-
What happens if a blocked tear duct is not treated?
The watering and discharge continue. Fluid sitting in the tear sac makes repeated infections of the sac (dacryocystitis) and conjunctivitis more likely. An infected sac forms a painful red swelling at the inner corner of the eye and needs antibiotic treatment.
-
Will the watering stop straight after surgery?
Not always. Swelling and the tube can keep the eye watering for a while. How long tear drainage takes to settle varies from person to person, and whether the new channel stays open is checked at follow-up visits after the tube has been removed.
- Published
- Last updated
Appointment
Would you like more information?
A short form about Blocked Tear Duct Surgery. We reply during working hours.
Treatments often evaluated together
-
Eyelid Surgery (Blepharoplasty)
Blepharoplasty removes excess skin and fat from the eyelids. When drooping skin narrows your field of vision, the operation also has a functional purpose.
-
Dry Eye Treatment
Causes of dry eye, the tear tests done at examination, choosing artificial tears, lid hygiene, punctal plugs and dry eye checks before laser surgery.
The first step is an examination.
Your details reach Dr. Yeşilkaya's team, and we will get back to you during working hours.
+90 537 858 78 07